
neck pain treatment
Neck Pain Treatment: A Decision Guide for Choosing Your Next Step

Start with the decision, not a single treatment
Neck pain treatment is a source-and-function decision, not a search for one remedy that fits every case. Your next step depends on how the pain began, how long it has lasted, whether it travels into an arm, whether you have changes in strength or sensation, and how much it interferes with sleep, work, driving, or ordinary movement.
Neck pain can arise from many different problems. That range explains why a treatment that makes sense for one symptom pattern may be poorly matched to another. A careful history and examination should come before a confident treatment choice.
A practical way to organize your options is to move through four questions:
- Is there a warning sign? If so, the priority is timely medical evaluation rather than routine self-management.
- Does the pattern appear uncomplicated? General activity, heat, education, and an active rehabilitation plan may be reasonable categories to discuss.
- Has the problem persisted or limited function? Persistence changes the value of a structured evaluation and a more specific plan.
- Would testing or an injection change the plan? Imaging and procedures have a role in selected situations, not as automatic steps.
This approach keeps treatment connected to the problem it is meant to address. It also helps you distinguish an option worth discussing from an option that has simply received more attention.
Your goal is not to identify a procedure from a list. Your goal is to identify the next decision that will give you clearer information or support a defined functional aim. That may mean monitoring a stable episode, arranging an evaluation, or discussing a targeted option after the clinical picture is clearer.
Separate routine symptoms from warning signs
Warning signs change the order of decisions because neck pain can sometimes accompany conditions that need closer evaluation. Clinical guidance identifies traumatic injury, infection, malignancy, vascular emergencies, and inflammatory conditions among the concerns that clinicians try to recognize through the history and examination.
New weakness, numbness, or a meaningful change in function deserves attention, particularly when a clinician suspects spinal-cord involvement. A clinical review describes suspected myelopathy with new neurological signs or symptoms as a situation that may warrant emergency referral; long-lasting symptoms with suspected myelopathy may warrant urgent referral.
A warning sign does not automatically mean an emergency. The appropriate pathway can range from monitored treatment to urgent or emergency referral, depending on the level of concern and the full clinical picture. That distinction matters because the same symptom label can lead to different actions after a clinician considers its onset, progression, associated findings, and examination.
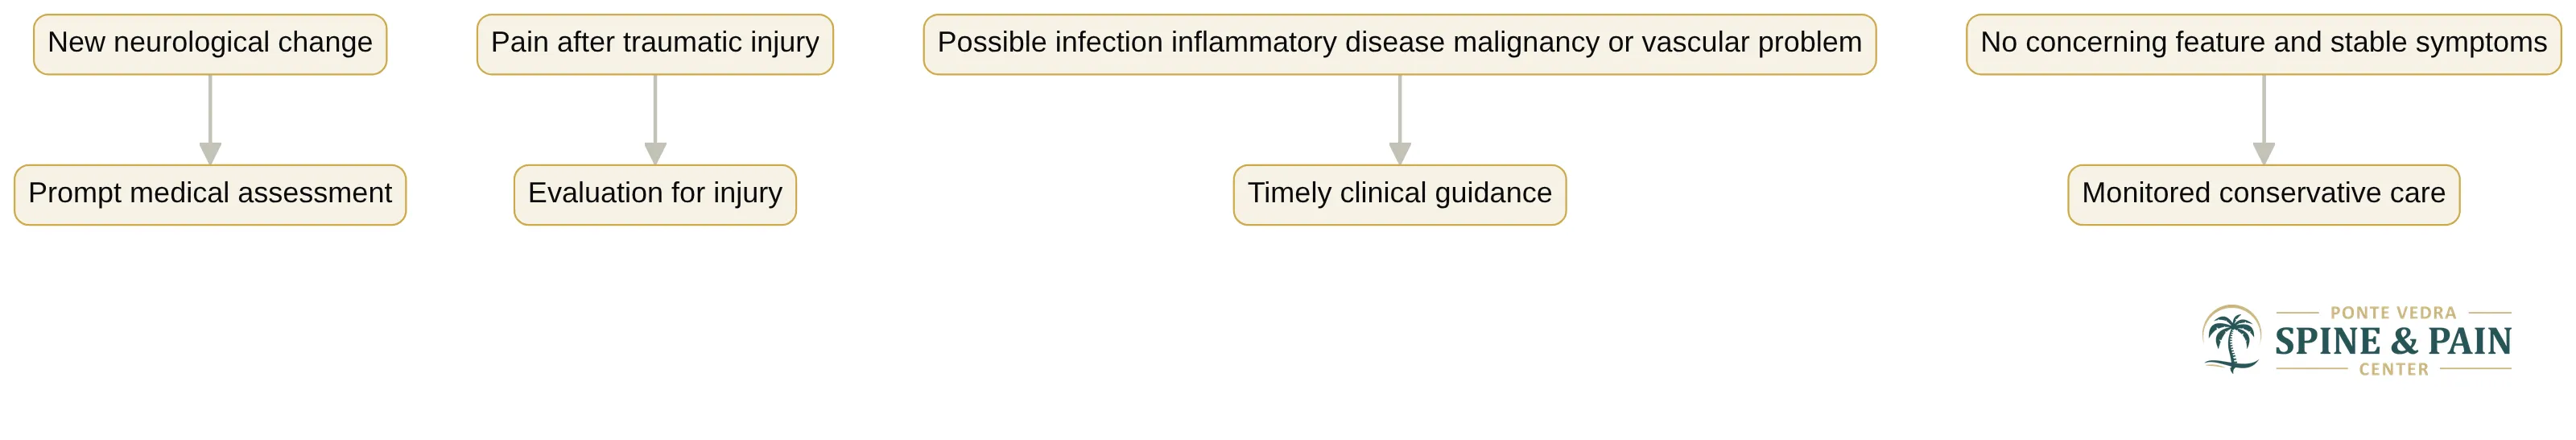
Use this sequence if your neck pain comes with a concerning change:
- New neurological change: seek prompt medical assessment rather than beginning a routine exercise or injection discussion on your own.
- Pain after traumatic injury: obtain an evaluation that considers injury before treating the symptoms as ordinary mechanical neck pain.
- Possible infection, inflammatory disease, malignancy, or vascular problem: seek timely clinical guidance so the cause can be assessed.
- No concerning feature and stable symptoms: discuss a monitored trial of conservative care, while paying attention to unexpected changes.
Do not use a general treatment guide to decide that a warning sign is harmless. If the pattern is changing quickly or neurological function is newly affected, the priority is evaluation.
Prompt evaluation does not predetermine the eventual treatment. It establishes whether routine self-management remains reasonable or whether the situation needs a different pathway. If you are unsure how concerning a new symptom is, describe it to a qualified healthcare professional rather than relying on a symptom list alone.
Use history and examination to define the problem
The history is central because timing, triggers, location, progression, and associated symptoms help establish which possibilities deserve attention. The physical examination adds important information, although examination findings may not identify the cause by themselves.
Prepare to describe the details that can change the treatment pathway:
- Onset: whether the pain began after an injury, a new activity, or without an obvious trigger.
- Pattern: whether it stays in the neck, travels toward an arm, or changes with position or movement.
- Time course: whether it is improving, stable, recurring, or gradually becoming more limiting.
- Function: which tasks are harder, including work at a desk, driving, sleep, lifting, or turning your head.
- Associated changes: whether you have noticed numbness, weakness, or another new neurological symptom.
- Previous care: what you have already tried and how your symptoms responded.
These details help separate a question about symptom control from a question about diagnosis. They also help clarify whether a clinician should focus first on education and rehabilitation, medication, selective testing, or another treatment category.
A treatment label cannot tell you what is causing your neck pain. The same broad complaint may reflect different clinical patterns, so your history and examination should guide the next step rather than the name of a procedure.
Function deserves specific attention during this conversation. Saying that you have pain gives less direction than explaining that you cannot turn your head while driving, sit through a workday, sleep in your usual position, or complete a familiar activity. Those details help connect the clinical discussion to a measurable reason for treatment.
Choose self-management for appropriate uncomplicated cases
Self-management is most appropriate when your symptoms appear uncomplicated, no warning sign is present, and your function is stable. Guidelines support physical activity for nonspecific neck pain, while one cited guideline recommends self-applied heat and notes that the evidence for thermotherapy’s effectiveness is weak.
A reasonable self-management discussion can include:
- Staying physically active within your current tolerance rather than treating prolonged inactivity as the default.
- Using self-applied heat if it provides comfort and fits your circumstances.
- Learning which movements or positions aggravate symptoms without assuming that every uncomfortable movement signals damage.
- Tracking whether function is improving, unchanged, or declining over time.
- Setting a point at which persistent or worsening symptoms prompt an evaluation.
The purpose of this approach is not to force you to manage every episode without professional input. It is to give uncomplicated symptoms a proportionate starting point while keeping the plan responsive to change. A guideline review describes monitored treatment as one possible pathway when concerning features are absent or limited.
Immobilization is not recommended for nonspecific neck pain in the cited guideline. That recommendation does not mean every movement is appropriate for every condition; it means routine immobilization should not replace an evaluation of the actual symptom pattern. If activity produces a new neurological change or a substantial decline in function, stop treating the episode as routine and seek medical guidance.
Self-management also needs a reassessment point. If symptoms remain stable and your function is returning, continue the agreed approach. If symptoms recur, stop improving, or begin interfering with work, sleep, driving, or ordinary movement, move from observation toward a structured evaluation. The change in function is the reason to reconsider the pathway.
Make rehabilitation active and individualized
Rehabilitation for neck pain should be active and individualized rather than reduced to a single exercise selected from a list. For nonspecific neck pain, guidelines support physical activity but do not establish one exercise type as generally preferred for everyone. Your preferences and the way your symptoms respond therefore matter when a rehabilitation plan is built.
An active plan may involve learning how to move, gradually restoring useful activity, and understanding which symptoms should change the plan. The exact exercises should follow the clinical pattern being addressed. A routine designed for uncomplicated stiffness is not automatically appropriate when pain follows trauma or accompanies neurological changes.
Guideline reviews support education and exercise interventions. They also support manual therapy when it is combined with active treatment, rather than treating hands-on care as the entire plan.
Use these questions to make a rehabilitation discussion more precise:
- What functional task are you trying to restore?
- Which movements can you perform now, and which ones consistently increase symptoms?
- How will you recognize progress besides measuring pain intensity?
- What should you do if numbness, weakness, or function changes?
- When should the plan be reassessed if progress stalls?
The most useful rehabilitation plan is one you can understand, perform, and relate to a defined functional goal. It should also include a clear boundary for reassessment when the pattern changes.
A plan can be adjusted without abandoning active care. The relevant question is whether the selected activity matches your symptoms and supports the function you want to regain. If the response is consistently unfavorable or neurological findings emerge, the plan needs clinical review rather than a stronger version of the same exercise.
Treat medication as a clinician-guided category
Medication can be part of neck pain treatment, but the appropriate choice depends on the type and duration of pain and on your health history. Pharmacology guidance describes acetaminophen and nonsteroidal anti-inflammatory drugs, or NSAIDs, as first-line options for most patients with acute mild-to-moderate pain. That statement does not establish that either option is appropriate for you.
The same guidance advises caution with nonselective NSAIDs if you have a history of gastrointestinal bleeding, cardiovascular disease, or chronic renal disease. Other medical factors can also change the medication discussion. Give the clinician or pharmacist a complete list of your diagnoses, allergies, and current medicines before starting, stopping, or combining pain medicines.
Medication conversations should cover more than the name of a drug. Ask about:
- The symptom pattern the medicine is intended to address.
- How long it should be considered before the plan is reassessed.
- Which health conditions or current medicines affect the choice.
- What changes should prompt you to stop and seek advice.
- Whether the medicine is meant to support movement and rehabilitation rather than replace them.
For mechanical or nonneuropathic neck pain, treatment may include short-term medication use and, in some cases, injections. Long-term evidence for these interventions is limited. That limitation supports a time-limited, purposeful discussion rather than indefinite medication use without reassessment.
Do not choose a dose or schedule from a general article. Medication suitability and instructions require clinical judgment based on your circumstances.
Medication is also only one part of the decision. A clinician may need to clarify whether your symptoms are acute or persistent, whether they are mechanical or associated with neurological findings, and whether the medicine would support a larger rehabilitation plan. Bring those questions to the appointment instead of treating a general category as a personal instruction.
Use imaging selectively
Imaging for neck pain should answer a clinical question rather than serve as an automatic first step. Imaging and electrodiagnostic testing do not have the same value in every case, especially when symptoms are chronic or degenerative. Guideline reviews support using imaging selectively, particularly when warning signs are present or when the result is likely to change management.
That principle creates a useful test before requesting a scan: What decision would the result change? The answer may relate to a suspected injury, a new neurological finding, or a treatment decision that requires more information. If the result would not change the next step, immediate testing may add information without clarifying the plan.
Your history and examination help determine whether imaging is relevant. Chronic or degenerative findings can be difficult to connect to pain without considering the full pattern, function, and examination.
Discuss imaging when:
- Symptoms follow trauma or include warning signs.
- Neurological function is changing.
- Symptoms persist and the result could alter treatment.
- A clinician is considering an intervention that requires more specific information.
Use selective imaging as a way to connect testing with action. It is not a way to avoid evaluation, and it is not a substitute for explaining how your symptoms behave.
The question is not whether imaging can show an abnormality. The question is whether the finding would help explain the clinical pattern or change what happens next. That distinction can keep testing connected to a decision rather than separating it from the examination.
Consider injections only within a broader plan
Injections may have a role in selected neck pain cases, but they should follow a clinical assessment and a defined treatment purpose. Guidance describes short-term medication use and possibly injections as options for some mechanical or nonneuropathic neck pain, while noting that long-term data for these interventions are limited.
Epidural steroid injections may be considered for carefully selected patients who do not improve with more conservative care. The cited guidance describes injections as one part of a broader treatment plan rather than a stand-alone approach, and it notes that their effect may be limited when they are used alone.
Before discussing an injection, clarify five points:
- The target: what structure or symptom pattern the injection is intended to address.
- The reason now: why the procedure is being considered at this point rather than continued rehabilitation, medication review, or observation.
- The expected role: whether it is intended to support movement, reduce a specific symptom, or help inform the next decision.
- The surrounding plan: what active treatment, education, or follow-up accompanies it.
- The reassessment point: how you and the clinician will decide whether the plan is helping.
An injection is not a diagnosis. It is a treatment category whose suitability depends on the suspected source, symptom persistence, functional effect, prior care, and examination. If those details are unclear, the next step is a clinical discussion rather than choosing a procedure from a list.
A procedure should therefore fit into a sequence of decisions. First clarify the symptom pattern and treatment goal. Then establish why the proposed injection is being considered, what other care accompanies it, and what result would lead to a different next step. This keeps the discussion focused on your function and clinical question.
Match the pathway to persistence and function
Persistence and function help determine whether you should continue monitoring, arrange an evaluation, or discuss a more specific treatment pathway. A short-lived episode with stable function and no warning sign can often begin with education, activity, heat, and observation. Symptoms that recur, remain limiting, or fail to follow the expected course deserve a more structured review.
Use the following decision path:
- Stable and improving: continue the agreed self-management or rehabilitation approach, and keep track of function as well as discomfort.
- Stable but persistent: arrange an evaluation to review the history, examination, previous care, and possible next categories rather than repeatedly changing treatments without a clear reason.
- Recurrent or function-limiting: discuss how work, sleep, driving, exercise, or ordinary movement is affected and whether a more specific evaluation could change management.
- Worsening or neurologically changing: seek prompt medical assessment, because a changing neurological pattern can require a different level of attention.
- Concerning from the beginning: prioritize evaluation for possible injury, infection, malignancy, vascular emergency, inflammatory disease, or suspected myelopathy.
This pathway does not rank one treatment above another. It matches the intensity of the next decision to the information available and the effect the symptoms are having on your life. Guideline reviews support education and exercise, selective testing, and carefully chosen interventions, but they do not make every option appropriate for every presentation.
Keep a brief record before an appointment:
- When symptoms occur and what brings them on.
- Whether the symptoms travel beyond the neck.
- Changes in strength, sensation, movement, or coordination.
- Which activities have become difficult.
- What you have tried and what happened afterward.
That record gives the evaluation a practical focus: not only where your neck hurts, but what the problem prevents you from doing.
Duration alone does not determine the pathway. A persistent symptom that is steadily improving may call for a different conversation than a shorter episode that is worsening or affecting neurological function. Describe both the time course and the direction of change.
What a Ponte Vedra Beach pain-clinic visit can clarify
A Ponte Vedra Beach pain-clinic visit can help connect your daily limitations with questions about evaluation and treatment. The discussion can organize what is known, what remains uncertain, and which next decision requires clinical judgment before testing or an intervention is considered.
A useful visit does not require you to arrive with a diagnosis. It can sort the discussion into three related questions:
- Does the pattern need prompt attention? A recent injury, new neurological change, or concern for infection, malignancy, vascular emergency, inflammatory disease, or myelopathy changes the priority. The appropriate response depends on the clinical concern; it may involve monitored care, urgent referral, or emergency referral.
- What pattern is being evaluated? Location, spread, onset, duration, progression, associated symptoms, and functional effect help distinguish a stable uncomplicated episode from a persistent, recurrent, or function-limiting problem. Examination findings add information, but they may not identify the cause by themselves.
- Which decision would change management? The answer may concern active rehabilitation, medication, selective imaging, or an injection considered after conservative care. Imaging is more useful when its result could change management. An injection should have a defined purpose and fit within a broader plan rather than stand alone.
This structure keeps a treatment category from becoming a diagnosis. It also prevents a scan, medicine, or procedure from carrying more meaning than the clinical question supports. For example, a chronic or degenerative pattern may not make imaging equally useful in every case. A medication discussion must account for individual health factors, and acute mild-to-moderate pain is the context in which pharmacology guidance describes acetaminophen and NSAIDs as first-line options for most patients. A clinician or pharmacist must determine whether that general information applies to you.
The conversation can also distinguish an active plan from passive symptom management. Guideline reviews support education and exercise, and manual therapy when combined with active treatment. For nonspecific neck pain, the cited guidance supports physical activity without identifying one exercise type for everyone. It also recommends against immobilization and notes weak evidence for heat’s effectiveness while recommending self-applied heat in that context. These points do not create a personal program; they give the appointment a framework for discussing what fits your presentation and preferences.
If an injection is raised, ask how it relates to the symptom pattern, what conservative care has already been tried, what role it is intended to serve, and what follow-up would determine the next decision. The cited guidance describes epidural steroid injections for carefully selected patients who do not improve with more conservative care, as part of a broader treatment plan. That context is more informative than treating injections as a separate answer to neck pain.
A focused appointment therefore has two outputs: a clearer description of the problem and a reasoned next step. Sometimes that step is continued monitoring; sometimes it is rehabilitation, medication review, selective testing, or discussion of an intervention. If the pattern is changing or function is declining, the need for reassessment takes priority over extending a routine plan.
Bring information that makes the visit specific:
- The date or approximate period when your symptoms began.
- Any injury, change in activity, or event that preceded them.
- The location and spread of the symptoms.
- Any change in strength, sensation, movement, or daily function.
- Previous medicines, exercises, therapy, tests, or injections.
- The tasks you most want to resume or perform more comfortably.
Useful questions include:
- What possible sources fit this symptom pattern?
- Which findings would change the urgency of evaluation?
- Is imaging likely to change the next decision?
- Which active treatment should be tried or continued first?
- If an injection is discussed, what is its specific purpose and how does it fit into the broader plan?
- When should the plan be reassessed?
A pain-clinic discussion should connect a proposed treatment to a defined clinical question. For example, an injection should have a stated purpose, a surrounding plan, and a way to judge whether the next step remains appropriate. If the evaluation identifies warning signs, the pathway may instead require urgent or emergency care.
For adults in Ponte Vedra Beach and nearby St. Johns County, a local evaluation can make the conversation more practical by focusing on the symptoms that are affecting your work, sleep, mobility, and daily routines.
You can make the visit more efficient by bringing prior test reports, a current medication list, and a short timeline of symptom changes when those records are available. The most useful preparation is specific: describe what changed, what you tried, and which activity you want to address first.
Know the limits of general treatment information
General neck pain information can organize choices, but it cannot identify your pain source from symptoms alone. The same complaint may call for different next steps depending on the history, examination, duration, functional effect, neurological findings, and warning signs.
Keep these boundaries in view:
- A treatment category is not a diagnosis.
- A scan is not automatically the explanation for pain.
- An exercise list is not a personalized rehabilitation plan.
- A medication name is not an instruction for your dose or schedule.
- An injection discussion does not establish that a procedure is appropriate.
- A warning sign requires attention to the full clinical picture, not a decision based on one phrase.
Guidelines support selective imaging, active treatment, and carefully chosen interventions, but they also preserve clinical judgment when warning signs or changing neurological findings are present. A red flag may lead to monitored treatment, urgent referral, or emergency referral depending on the concern. That range is why your next step should follow an assessment rather than a universal rule.
Use general information to prepare better questions and describe your symptoms more clearly. Use an evaluation to decide which category fits your circumstances.
The most useful boundary is practical: general information can help you organize a conversation, but your symptoms, examination, medical history, and functional goals determine what advice applies to you.
Choose your next step for neck pain in Ponte Vedra Beach
The right next step for neck pain depends on the source suggested by your history and examination, the duration and progression of symptoms, and the effect on your function. Stable, uncomplicated symptoms may begin with activity, heat, education, and active rehabilitation. Persistent, recurrent, or function-limiting symptoms may justify a structured evaluation. New neurological changes, pain after injury, or other concerning features call for prompt medical attention.
A qualified healthcare professional must determine your individual suitability for medication, testing, rehabilitation, or an injection. Bring a clear account of when your symptoms began, what they prevent you from doing, and what you have already tried. That information makes the next conversation more focused.
At Ponte Vedra Spine & Pain Center, located at 380 Town Plaza Ave, Suite 420, Ponte Vedra Beach, FL 32081, we can discuss persistent, recurrent, or function-limiting neck pain in the context of your symptoms and daily function. A focused conversation can help you identify which questions require clinical attention and which next step fits the information available.
When should neck pain be evaluated promptly?
When should I seek medical evaluation for neck pain?
You should seek medical evaluation for neck pain if you experience new neurological symptoms, pain following a significant injury, or if there are signs of infection, malignancy, or other serious conditions.
How does the evaluation process for neck pain typically work?
A neck pain evaluation typically involves discussing your symptoms and medical history, followed by a physical examination to assess tenderness, numbness, weakness, and neck movement.
What role does imaging play in neck pain diagnosis?
Imaging for neck pain should be used selectively, primarily when there are warning signs or when the results are likely to change management. It is not an automatic first step.
What should I consider before discussing injections for neck pain?
Before discussing injections, clarify the target symptom, the reason for considering the injection now, its expected role in your treatment plan, and how you will assess its effectiveness.
How can I prepare for a visit to a pain management clinic for neck pain?
Prepare for your visit by bringing a timeline of your symptoms, any previous treatments you’ve tried, and specific questions about your condition and treatment options.
Living with this?
We treat this in Ponte Vedra Beach.
Dr. Eli Loch, D.O. — double board-certified in anesthesiology and pain medicine. Reading about it only goes so far; a diagnosis tells you which of these actually applies to you.